Introduction
- Diphyllobothrium latum, commonly known as the broad fish tapeworm, is a parasitic flatworm that infects humans.
- It belongs to the phylum Platyhelminthes and class Cestoda.
- The parasite primarily lives in the small intestine of humans and other fish-eating mammals.
- Humans become infected by consuming raw or inadequately cooked freshwater fish containing infective larvae.
- The infective stage for humans is the plerocercoid larva.
- Its life cycle involves two intermediate hosts: a copepod (small freshwater crustacean) and a freshwater fish.
- The infection caused by this parasite is known as diphyllobothriasis.
- In some infected individuals, the parasite may contribute to vitamin B12 deficiency, which can lead to megaloblastic anemia.
- Diagnosis is mainly performed by microscopic examination of stool for characteristic operculated eggs.
Habitat and Distribution
Morphology
- General appearance: Diphyllobothrium latum is a long, ribbon-shaped, segmented parasitic flatworm commonly known as the broad fish tapeworm.
- Length: The adult worm may reach approximately 10 metres or more in length.
- Body parts: The body consists of three main parts: scolex, neck, and strobila.
- Scolex: The scolex is the head region and is elongated and spoon-shaped.
- Bothria: The scolex possesses two longitudinal sucking grooves called bothria, which help the parasite attach to the intestinal mucosa.
- Hooks and suckers: The scolex lacks hooks and the four typical cup-shaped suckers found in many other tapeworms.
- Neck: The neck is a narrow region behind the scolex that produces new body segments.
- Strobila: The strobila is the long, segmented body consisting of numerous proglottids.
- Proglottids: The mature proglottids are generally broader than they are long and contain both male and female reproductive organs.
- Uterus: The uterus in mature proglottids typically forms a characteristic rosette-shaped structure.
- Eggs: The eggs are oval, yellowish-brown, and operculated, meaning they possess a lid-like structure at one end.
Epidemiology
- Geographic Distribution:
- D. latum is found worldwide, with high prevalence in areas where raw or undercooked freshwater fish is commonly consumed.
- It is most common in northern Europe, Russia, Asia, and North America, where traditional diets involve the consumption of raw or inadequately cooked fish.
- In some parts of the world, the parasite is also common in South America, particularly in regions where freshwater fish are part of the local diet.
- Transmission:
- Humans become infected by eating raw, undercooked, or pickled freshwater fish containing infected plerocercoid larvae (the infective stage).
- Fish-eating mammals (definitive hosts) release proglottids containing eggs into the water via feces, where they hatch and develop into larvae.
Life Cycle
The life cycle of D. latum involves multiple hosts and stages: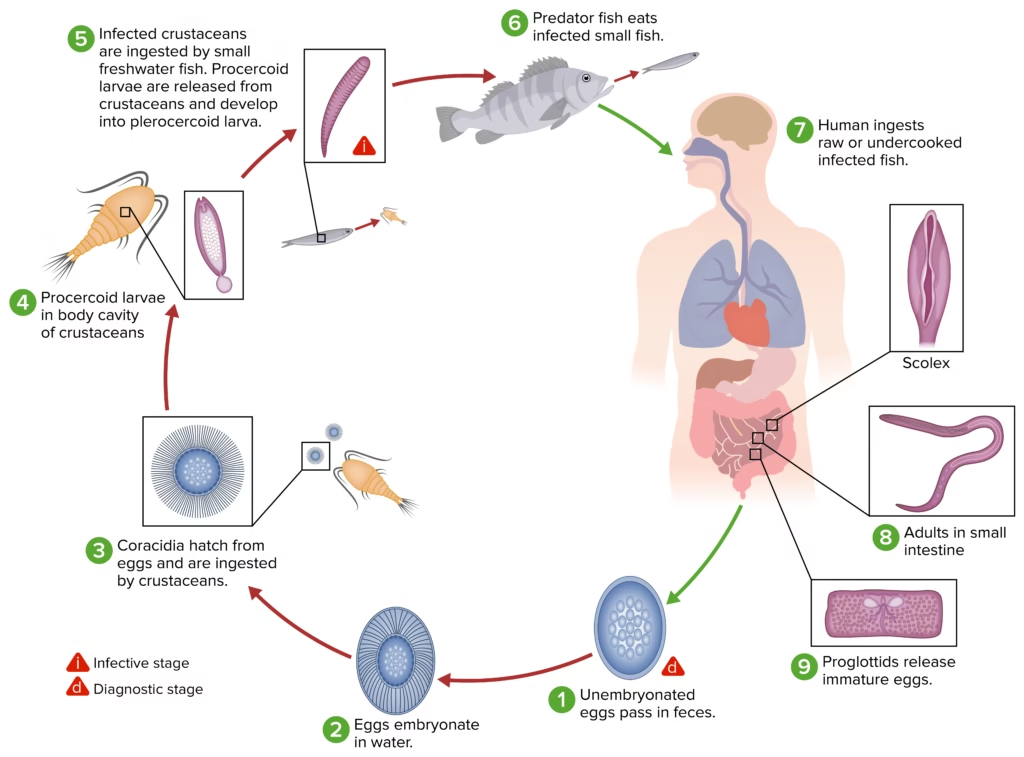
1. Eggs Passed in Feces
- The adult tapeworm lives in the small intestine of humans.
- Eggs are released from the adult worm and passed out of the body through feces.
- The eggs reach freshwater and develop under suitable environmental conditions.
2. Development of Coracidium
- In freshwater, the eggs embryonate and hatch.
- A small, ciliated larva called a coracidium emerges from the egg.
- The coracidium swims freely in the water.
3. First Intermediate Host: Copepod
- A small freshwater crustacean called a copepod ingests the coracidium.
- Inside the copepod, the larva develops into a procercoid larva.
- The copepod acts as the first intermediate host.
4. Second Intermediate Host: Freshwater Fish
- A freshwater fish consumes the infected copepod.
- The procercoid larva penetrates the fish’s tissues.
- It develops into a plerocercoid larva, the infective stage for humans.
- Larger predatory fish may also become infected by eating smaller infected fish.
5. Infection of Humans
- Humans become infected by consuming raw or inadequately cooked freshwater fish containing viable plerocercoid larvae.
- The larvae are released during digestion and reach the small intestine.
6. Development of Adult Worm
- The plerocercoid larva attaches to the mucosa of the small intestine.
- It develops into an adult tapeworm.
- The adult worm produces eggs, which pass out of the body through feces and continue the life cycle when they reach suitable freshwater conditions.
Pathogenesis
- Pathophysiology:
- The adult tapeworm lives in the small intestine, which can grow up to several meters long. The scolex (head) of the worm attaches to the intestinal wall, where it absorbs nutrients from the host.
- The parasite does not typically invade host tissues but may cause a range of symptoms due to its size and presence in the intestines.
- Symptoms:
- In many cases, D. latum infections are asymptomatic or cause mild gastrointestinal symptoms.
- Symptoms may include:
- Abdominal discomfort
- Nausea
- Diarrhea
- Weight loss
- Fatigue
- B12 deficiency (in some cases) can lead to anemia due to the worm’s ability to absorb vitamin B12 from the host.
- Rarely, the infection can cause intestinal obstruction, especially in heavy infestations.
- Complications:
- Vitamin B12 deficiency may lead to megaloblastic anemia in chronic infections.
- Intestinal obstruction may occur in cases of large worm burdens.
- Perforation of the intestine is a rare but severe complication.
Laboratory Diagnosis
1. Stool Examination
A. Macroscopic Examination
- The stool sample is examined for visible tapeworm segments (proglottids).
- Adult worm segments may occasionally be observed in the stool.
- The presence of segments may raise suspicion of an intestinal tapeworm infection.
B. Microscopic Examination
- Stool microscopy is the primary diagnostic method.
- Oval or elliptical, yellowish-brown eggs may be observed.
- The eggs possess an operculum (lid-like structure) at one end.
- A small knob may be present at the opposite end.
- Detection of characteristic eggs supports the diagnosis.
2. Identification of Proglottids
- Proglottids may be examined microscopically for species identification.
- Mature segments are generally broader than they are long.
- The uterus typically has a characteristic rosette-shaped appearance.
- These morphological features help differentiate the parasite from other tapeworms.
3. Complete Blood Count (CBC)
- A CBC may be performed to evaluate suspected anemia.
- Hemoglobin may be decreased if anemia develops.
- Mean corpuscular volume (MCV) may be increased in megaloblastic anemia.
- A peripheral blood smear may show macro-ovalocytes and hypersegmented neutrophils.
4. Serum Vitamin B12 Estimation
- Serum vitamin B12 levels may be measured when deficiency is suspected.
- Reduced vitamin B12 levels may be associated with prolonged infection in some patients.
- Vitamin B12 deficiency can contribute to megaloblastic anemia and neurological manifestations.
5. Biochemical Investigations
Additional biochemical tests may help evaluate vitamin B12 deficiency.
- Serum methylmalonic acid: May be increased in vitamin B12 deficiency.
- Serum homocysteine: May be increased in vitamin B12 deficiency.
- Serum folate: May be measured to help assess other causes of megaloblastic anemia.
These tests assess associated nutritional complications rather than directly identifying the parasite.
6. Molecular Diagnosis
- Molecular techniques, such as polymerase chain reaction (PCR), may be used in specialized laboratories.
- These methods can help identify the parasite at the species level.
- They may be useful when routine morphological identification is inconclusive.
Summary Table: Diphyllobothrium latum
| Aspect | Description |
| Habitat | The small intestine of humans (definitive host) and carnivorous mammals. Fish and copepods serve as intermediate hosts. |
| Epidemiology | Found in areas with raw or undercooked freshwater fish consumption. Common in northern Europe, Russia, Asia, and North America. |
| Morphology | Adult: Long (up to 10 m), flattened, with a scolex and two sucking grooves (bothria). Eggs: Oval, operculated, with a coracidium. |
| Life Cycle | Eggs hatch into coracidia in water, ingested by copepods and fish. Humans ingest infected fish, where the larvae mature into adults in the small intestine. |
| Pathogenesis | Mostly asymptomatic, but can cause abdominal discomfort, nausea, and B12 deficiency leading to anemia. Heavy infections can lead to intestinal obstruction. |
| Laboratory Diagnosis | Microscopic stool examination for eggs, fecal flotation techniques, PCR for detection of larvae, serology, and endoscopic examination in severe cases. |
Prevention and Control
1. Proper Cooking of Fish
- Cook freshwater fish thoroughly before consumption.
- Avoid eating raw or inadequately cooked fish that may contain infective plerocercoid larvae.
- Ensure that fish is adequately heated throughout to kill the parasite larvae.
2. Proper Freezing of Fish
- Use recognized time and temperature combinations for freezing fish intended to be eaten raw or undercooked.
- Do not assume that ordinary refrigeration or freezing under uncontrolled conditions will kill all parasite larvae.
- Follow established food-safety guidelines for effective parasite control.
3. Maintenance of Personal Hygiene
- Wash hands thoroughly after using the toilet and before handling food.
- Maintain proper hygiene while preparing and handling fish.
- Avoid contamination of food and water with fecal material.
4. Proper Sanitation
- Ensure safe disposal and treatment of human waste.
- Prevent human feces from entering freshwater bodies.
- Maintain adequate sewage treatment systems to interrupt the parasite’s life cycle.
5. Safe Food Handling
- Purchase fish from reliable sources.
- Use clean utensils and preparation surfaces.
- Prevent cross-contamination between raw fish and ready-to-eat foods.
- Follow recommended fish-processing and storage practices.
6. Health Education and Awareness
- Educate people about the risks of consuming raw or inadequately cooked freshwater fish.
- Promote safe cooking and fish-processing practices.
- Increase awareness of the symptoms and complications of diphyllobothriasis.
7. Early Diagnosis and Treatment
- Identify infected individuals through appropriate stool examination.
- Treat confirmed infections with suitable antiparasitic medication under medical guidance.
- Evaluate patients for vitamin B12 deficiency when clinically indicated.
8. Public Health Measures
- Improve sanitation in communities near freshwater environments.
- Promote food-safety monitoring and safe fish-processing practices.
- Encourage appropriate surveillance in areas where fish tapeworm infections occur.